Choosing Between Two Good Options Instead of One Loud One
You’ve lost a tooth and someone has told you an implant is better. That advice skips the part that decides it, which is what your jaw and your neighboring teeth can support. An implant replaces the root. A bridge spans the gap by leaning on the teeth either side. Patients in Tewksbury usually arrive having read a comparison that picks a winner before anyone looked in their mouth. You’ll come away knowing what each one asks of you and what the survival research shows. The conditions that rule either one out are here too.
Dr. Elaine Wu, DMD, trained at Boston University and graduated with highest honors. She’s completed the 260-hour Kois Center program. Every case opens with a Kois-trained evaluation before anyone talks about a preference, including hers. That matters here, because getting this wrong costs you healthy tooth structure you can’t put back. Neither option is reversible once it’s done.
What Is The Actual Difference Between The Two?
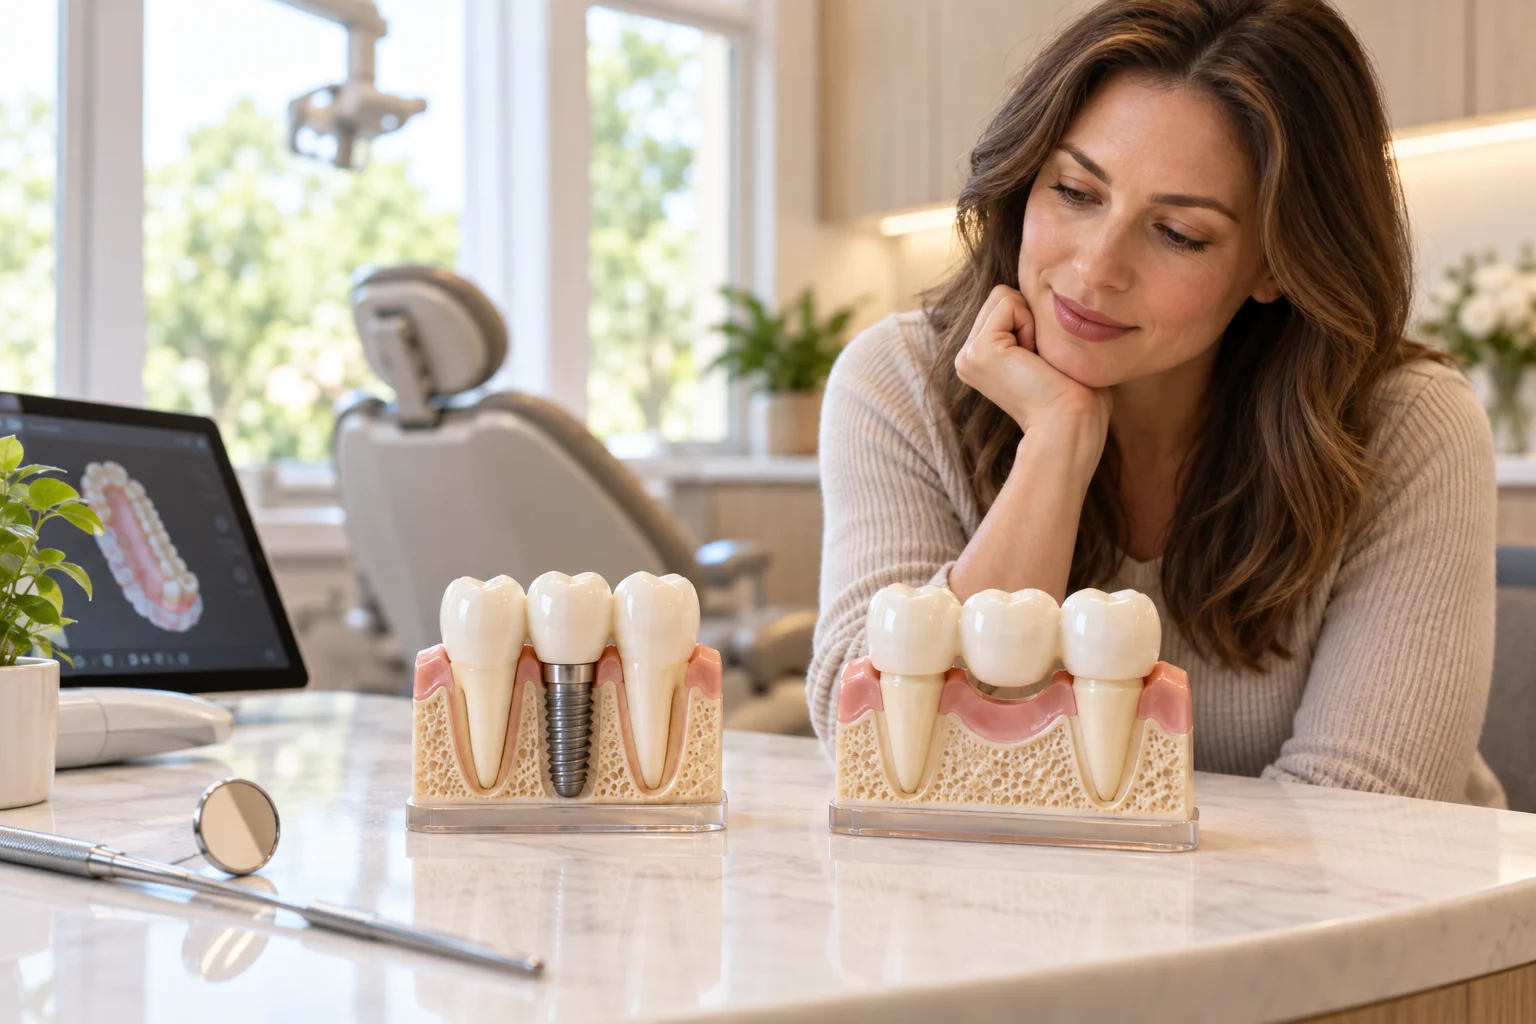
An implant is a titanium post placed into the jawbone. A crown goes on top of it. It replaces the root as well as the tooth, and it touches nothing beside it. A bridge works differently. It caps the sound teeth either side of the gap and hangs a replacement tooth between them. Cleveland Clinic notes a bridge most often spans one to three teeth and needs healthy natural teeth on both sides.
That structural difference drives everything else. An implant stays a one-tooth problem from start to finish. A bridge is a three-tooth commitment, since the two anchors get permanently reduced to carry crowns. Neither approach is a compromise. They solve the gap in different ways, and they suit different mouths for reasons you can see on an x-ray.
What Does The Research Say About How Long Each Lasts?
Both do well, and the gap between them is smaller than most comparison pages suggest. A systematic review of 18 prospective studies put ten-year implant survival at 96.4 percent. That drops to 91.5 percent in patients aged 65 and over. A separate meta-analysis put five-year survival of tooth-supported bridges at 93.8 percent. Implant-supported work came in at 95.2 percent.
Sources: Howe et al., Long-term 10-year dental implant survival, Journal of Dentistry, 2019. Pjetursson et al., Comparison of survival and complication rates of tooth-supported and implant-supported fixed dental prostheses, 2007.
Those are survival figures rather than promises to you. Results vary with bone quality, gum health, smoking, and how well the work is maintained. What the numbers do settle is that a bridge is not a short-term patch and an implant is not guaranteed. Anyone telling you otherwise is selling rather than planning.
Which One Is Right For My Mouth?
The honest answer starts with your bone, not your budget. An implant needs enough bone volume to hold the post. If the tooth has been gone a while, there may not be enough left. A bridge needs two sound anchors either side of the gap. Lose either condition and one option comes off the table before cost enters the conversation.
- Enough bone height and width, or willingness to have a graft first, points toward an implant.
- Teeth either side that already need crowns makes a bridge less wasteful, since they’re getting covered anyway.
- Untreated gum disease rules out both until it has been treated and stabilized.
- Smoking raises implant failure risk, so it gets discussed openly before any planning starts.
- A medical history affecting bone healing changes the implant conversation entirely.
Two people with the same missing tooth can get different recommendations, and that is the point rather than a contradiction. Our dental implants page covers what the placement involves once the bone question is settled.
 How Do They Compare Side By Side?
Read this against your own mouth rather than as a scoreboard. Each row is a real trade, and which side of it you want depends on what you’re starting with.
| Dental implant | Dental bridge | |
| What it replaces | The tooth and its root | The tooth only |
| Neighboring teeth | Untouched | Reduced and crowned |
| Bone underneath | Loaded, so it holds | Not loaded, so it keeps shrinking |
| Typical timeline | Months, with healing between stages | Weeks, usually two or three visits |
| If it fails | The neighbors are unaffected | The whole span usually comes off |
| Needs surgery | Yes | No |
The timeline row is the one patients weigh most and hear least about. A bridge is finished in weeks. An implant runs months because bone has to fuse to the post before anything loads it. Paying more doesn’t compress that, and our page on the dental implant procedure sets out each stage.
What Does Each One Ask Of You Afterward?
An implant is cleaned like a natural tooth, with attention to the gum margin where peri-implantitis starts. A bridge needs floss threaded underneath the span every day. The area beneath it traps food and cannot be reached any other way at all. Skip it and decay starts on the anchor teeth rather than the bridge itself. That’s the failure nobody sees coming.
That daily difference matters more than it sounds. Bridge failures usually trace back to the anchors rather than the bridgework. Anchors fail from decay that started under a span nobody cleaned. If threading floss daily isn’t realistic for you, say so during planning rather than afterward. It changes the recommendation, and nobody will think less of you for it.
When Do We Recommend Against Each One?
There are cases where we tell people no, and they cost us the case either way. Saying it upfront is cheaper for you than finding out at year three.
- Not enough bone for an implant, and no appetite for a graft first.
- Sound, untouched neighbors that a bridge would need to grind down for no other reason.
- Active periodontal disease, which rules out both until treated.
- Heavy grinding without a nightguard plan, which threatens either one.
- A gap at the very back of the arch with nothing behind it, which leaves a bridge no second anchor.
Cost sits inside all of this rather than above it. Current figures by treatment sit on our dental implant cost page. The sequence matters more than the headline number, since extractions and grafting are priced separately.
Find Out Which One Your Jaw Will Take
Patients reach us from Pinnacle Crossing and Merrimack Meadows. Others come along Route 129 where it ties into the north end of town. Most come in having already been told which option to pick, usually by someone who never saw an x-ray. Dr. Elaine Wu trained at Boston University with highest honors and completed the 260-hour Kois Center program. Every plan starts with imaging of the bone, because that is what narrows the choice rather than a preference.
One visit tells you which options your mouth will support and which it won’t. Call 978-451-1500 or book through mybrandnewsmile.com, and bring any recent x-rays you have. Chewing normally on that side again is the outcome, and results vary by case.
Questions Tewksbury Patients Ask
Why is a dental bridge not recommended?
It often is recommended, and the objection is specific rather than general. A traditional bridge requires cutting down two healthy teeth to carry crowns, and that tooth structure never grows back. Where those neighbors are already damaged or already crowned, the objection largely disappears. Mayo Clinic describes implant surgery as an option when dentures or bridgework fit poorly. That is a narrower claim than bridges being a bad idea.
Which is better, a bridge or an implant?
Neither, in the abstract. An implant preserves the neighboring teeth and the bone, and it takes months. A bridge is quicker and asks nothing of your jawbone, and it costs you two healthy teeth. The American Dental Association’s guidance on tooth replacement sets out the options without ranking them. The ranking depends on the mouth. Your bone volume and the state of the neighbors decide it.
What is more painful, a bridge or an implant?
Both are done under local anesthetic, and neither should hurt at the time. Recovery is where they differ. An implant leaves a surgical site that’s sore for a few days. A bridge leaves the prepared teeth sensitive for a week or two. Sedation is available for either one. Untreated gum disease makes both more uncomfortable. The NIDCR describes gum treatment as a deep cleaning below the gumline, and that comes first.
What do people wish they knew before dental implants?
Two things come up repeatedly in the chair afterward. The timeline is longer than expected, since bone needs months to fuse to the post before a crown goes on. An implant is also not immune to gum problems. The daily cleaning around it matters as much as it did before. Cleveland Clinic notes that bone grafting is sometimes needed first to provide a strong foundation. That adds a stage people rarely factor in.
Contact Us
Phone:
978-451-1500
Address:
1201 Main St.
Tewksbury, MA 01876
Email:
team@mybrandnewsimile.com